Long-Term Management and Treatment Strategies for Polypoidal Choroidal Vasculopathy
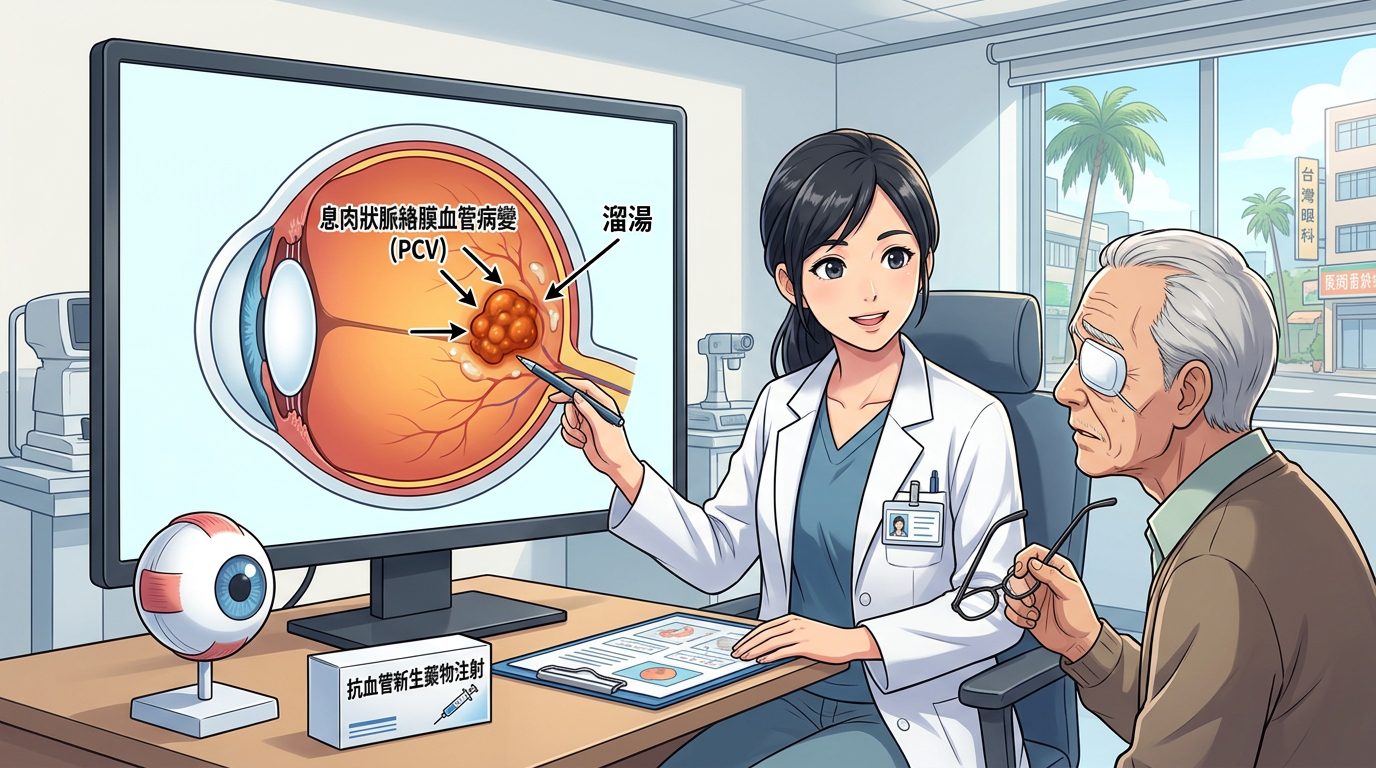
Summary of the Meeting Speaker 1 discussed the long-term challenge of preserving vision in PCV after an initial treatment response. The presentation moved from two contrasting patient cases to observational and clinical study findings, then to treatment intervals, recurrence risk, surveillance, and practical responses when disease activity returns. The central message was that longer dosing intervals can reduce treatment burden, but do not eliminate recurrence risk; sustained lesion control and useful vision over time remain the priorities. The presenter noted that there is no validated PCV stopping rule and recommended structured OCT follow-up, prompt assessment and retreatment of recurrence, and consideration of switching treatment or PDT when control remains inadequate. Topic 1: Long-Term Outcomes in Two Patient Cases
- Speaker 1 opened by thanking Adrien for organizing the course and introduced the focus: “practical challenges: how to preserve vision in PCV after the initial treatment response” [???].
- The presenter described two cases illustrating different long-term courses:
- The first patient maintained 20/25 vision in both eyes for 10 years, offered as an example of sustained disease control.
- The second patient had been followed for 13 years and received 82 injections. After an initially stable period, recurrences became more frequent.
- In the second case, increased macular thickness often coincided with declining visual acuity; vision had reached 20/200.
- The cases raised the question of whether worsening vision with repeated recurrence is an individual outcome or reflects a broader long-term pattern.
- Challenge identified: Long-term disease management can become more difficult as recurrences grow more frequent, and recurrent activity may be accompanied by loss of vision. Action items | Action item | Brief description | Responsible party | Time frame | Due date | Notes | | --- | --- | --- | --- | --- | --- | | Monitor long-term disease activity and vision | Track visual acuity, macular thickness, and recurrence over time in treated PCV. | Not assigned in the presentation | Ongoing | Not specified | Based on the contrast between the two cases; no specific monitoring schedule was provided. | | Open questions | | | | | |
- Do the worsening recurrences in the second case reflect a broader long-term PCV pattern or an individual course?
- What approaches can best preserve vision as recurrences become more frequent? Topic 2: Broader Long-Term Outcomes, Recurrence, and Atrophy
- Speaker 1 referred to a study by Pick and colleagues that included 258 eyes with PCV and 902 eyes with typical neovascular AMD.
- Both groups changed from baseline in visual acuity. The presenter said the PCV group had a better outcome, but that early gains gradually declined.
- The presenter cautioned that these were observational findings and that treatment varied, limiting interpretation.
- PCV was characterized as a relapsing disease. Recurrence estimates vary because definitions and follow-up periods differ, but renewed activity is common and can be hemorrhagic.
- The presenter emphasized that atrophy does not necessarily mean the underlying vascular complex has disappeared.
- Challenges identified:
- Differences in recurrence definitions and follow-up make recurrence estimates difficult to compare.
- Early visual gains may decline over time.
- Atrophy alone may not establish that the vascular lesion has resolved. Action items | Action item | Brief description | Responsible party | Time frame | Due date | Notes | | --- | --- | --- | --- | --- | --- | | Interpret long-term outcome data cautiously | Account for variable treatment and observational study design when applying the reported visual outcomes. | Not assigned in the presentation | When reviewing or applying the evidence | Not specified | No specific implementation owner was identified. | | Continue assessing for lesion activity when atrophy is present | Do not assume that atrophy means the vascular complex has disappeared. | Not assigned in the presentation | Ongoing, as clinically relevant | Not specified | The presenter did not specify a particular assessment protocol. | | Open questions | | | | | |
- How much of the gradual decline in early visual gains reflects recurrent activity, treatment differences, or other factors?
- How should recurrence be defined consistently across studies?
- What assessment is appropriate when atrophy is present but lesion activity remains a concern? Topic 3: Evidence and Ongoing Study of Treatment in Different Populations
- Speaker 1 asked about treatment outcomes in Caucasian and Asian populations and referred to the Atlantic study as a European reference.
- For aflibercept 2 mg, the presenter reported a gain of 6.3 letters at one year and complete polyp occlusion in 72% of patients.
- The presenter then discussed the ongoing Monte Carlo study, described as a phase 4 study examining faricimab in Caucasian patients with PCV.
- The study targets 120 patients across 31 European sites.
- The stated regimen includes four initiation doses, followed by individualized treat-and-extend treatment.
- Recruitment was ongoing, and the study was described as lasting two years.
- Efficacy results were still pending.
- Challenges identified: Evidence for faricimab in the described Caucasian PCV population was not yet available because the study was ongoing. The presentation did not provide comparative results between populations. Action items | Action item | Brief description | Responsible party | Time frame | Due date | Notes | | --- | --- | --- | --- | --- | --- | | Complete recruitment and follow-up for the Monte Carlo study | Conduct the ongoing phase 4 study of faricimab in Caucasian PCV patients under its stated protocol. | Study team; individual owner not named | Two-year study; recruitment ongoing at the time of the presentation | Not specified | Targets 120 patients at 31 European sites; efficacy results were pending. | | Review Monte Carlo efficacy results when available | Assess the study findings once reported. | Not assigned in the presentation | After results become available | Not specified | No publication or results date was given. | | Open questions | | | | | |
- How will faricimab perform in Caucasian patients with PCV?
- How will results compare across Caucasian and Asian populations?
- When will efficacy results from the ongoing study become available? Topic 4: Extended Dosing Intervals and Maintaining Disease Control
- Speaker 1 noted that longer dosing intervals may be feasible in selected PCV eyes, referring to data presented by Sadaka.
- A post hoc analysis of the PCV group in PULSAR included 139 eyes treated with aflibercept 8 mg:
- 52% had a last assigned interval of at least 20 weeks at year 3.
- In SALWIN, the presenter reported that:
- 61% of patients were assigned to 20-week dosing at week 104.
- 82% reached an interval of at least 12 weeks.
- Speaker 1 explicitly cautioned that the studies cannot be compared directly.
- The presenter emphasized that longer intervals matter only if vision and lesion control are maintained.
- For aflibercept 8 mg, the presenter cited a visual gain of 8.2 to 9.6 letters; the transcript does not clarify the specific time points or comparison represented by that range.
- For faricimab in SALWIN, patients maintained a 7.3-letter gain at two years. The presenter also referred to a reduction in central thickness and reported that among 84 patients assessed by ICG, 62% had complete polyp occlusion.
- Challenges identified:
- Interval outcomes across PULSAR and SALWIN should not be treated as directly comparable.
- Extending intervals is not, by itself, evidence of adequate treatment if vision or lesion control is not maintained. Action items | Action item | Brief description | Responsible party | Time frame | Due date | Notes | | --- | --- | --- | --- | --- | --- | | Individualize treatment intervals | Consider longer intervals for selected eyes while continuing to assess vision and lesion control. | Treating clinician; not individually assigned | Ongoing | Not specified | The presenter did not provide patient-selection criteria beyond “selected PCV eyes.” | | Avoid direct comparison of PULSAR and SALWIN interval results | Interpret each study within its own design and population. | Not assigned in the presentation | When reviewing the study data | Not specified | The presenter stated that the studies cannot be compared directly. | | Open questions | | | | | |
- Which clinical features identify patients who can safely maintain longer intervals?
- What level of lesion control and visual stability should be required before extending an interval?
- What were the specific time points or comparisons underlying the aflibercept 8 mg gain reported as 8.2 to 9.6 letters? Topic 5: Identifying Eyes That May Need Closer Surveillance
- Speaker 1 asked which eyes still require closer surveillance.
- Persistent polyps, cluster lesions, and greater lesion burden were identified as potential indicators of higher recurrence risk.
- The presenter described complete closure, a dry OCT, and stable vision as reassuring findings.
- However, Speaker 1 stated that no combination of biomarkers provides a valid stopping rule.
- Challenge identified: Favorable imaging and visual findings may be reassuring, but the presentation did not establish a validated way to determine when treatment can stop. Action items | Action item | Brief description | Responsible party | Time frame | Due date | Notes | | --- | --- | --- | --- | --- | --- | | Consider closer surveillance for higher-risk lesion features | Take persistent polyps, clustered lesions, and greater lesion burden into account when planning follow-up. | Treating clinician; not individually assigned | Ongoing | Not specified | These features were presented as possible risk indicators, not as a validated prediction rule. | | Do not use a biomarker combination as a stopping rule | Avoid treating reassuring findings as proof that treatment can safely be discontinued. | Not assigned in the presentation | When considering treatment cessation | Not specified | The presenter stated that no valid PCV stopping rule exists. | | Open questions | | | | | |
- How reliably do persistent polyps, clustered lesions, and lesion burden predict recurrence?
- Could a validated combination of imaging and clinical markers eventually support treatment cessation decisions?
- What surveillance schedule is appropriate for eyes with reassuring findings but ongoing recurrence risk? Topic 6: Responding to Recurrence and Long-Term Management
- Speaker 1 asked how to respond when recurrence occurs and outlined a practical approach:
- Confirm activity on OCT and assess for hemorrhage.
- Use ICG when lesion assessment would change management.
- Retreat promptly and shorten the interval to regain control.
- Extend again after stability is restored.
- If control remains inadequate, consider switching treatment or using PDT for persistent active polypoidal lesions.
- The presenter stressed that regaining control is the immediate priority.
- The long-term goal was described as preserving useful vision over years. Longer intervals can reduce treatment burden, but do not remove recurrence risk.
- Speaker 1 stated that there is no validated PCV stopping rule and that any treatment pause requires structured OCT follow-up and rapid access to treatment. The transcript’s wording around treatment pauses was unclear; no more specific pause protocol was provided.
- The presentation concluded that early detection of recurrence is important to prevent further vision loss.
- Challenges identified:
- Recurrence can occur despite extended intervals or apparently favorable findings.
- Inadequate control may require a change in treatment or PDT.
- Treatment cessation or pauses require follow-up arrangements, but no validated stopping rule or specific pause protocol was presented. Action items | Action item | Brief description | Responsible party | Time frame | Due date | Notes | | --- | --- | --- | --- | --- | --- | | Confirm suspected recurrence | Assess OCT for activity and check for hemorrhage. | Treating clinician; not individually assigned | When recurrence is suspected | Not specified | ICG was suggested when lesion assessment would change management. | | Restore control promptly | Retreat and shorten the interval; extend again after stability returns. | Treating clinician; not individually assigned | Promptly when recurrence is confirmed | Not specified | No exact interval or retreatment regimen was specified. | | Reassess inadequate control | Consider switching treatment or PDT for persistent active polypoidal lesions. | Treating clinician; not individually assigned | If control remains inadequate | Not specified | The presenter did not specify which treatment to switch to or PDT criteria. | | Ensure follow-up during any treatment pause | Arrange structured OCT follow-up and rapid access to treatment. | Not assigned in the presentation | During any treatment pause | Not specified | No validated PCV stopping rule or detailed pause protocol was provided. | | Open questions | | | | | |
- What specific criteria should trigger a treatment switch or PDT?
- What OCT follow-up schedule and access arrangements are appropriate during a treatment pause?
- How should treatment pauses be managed in the absence of a validated stopping rule?
- What is the best way to detect recurrence early enough to prevent further visual loss?
延伸閱讀
2026-10月, 歐洲Euretina視網膜醫學會-黃奕修教授會後新知與心得分享: 認識CSC中心性漿液性脈絡膜視網膜病變 (中漿病) (一般民眾版)
中心性漿液性脈絡膜視網膜病變常造成黃斑部積水而影響視力。多數急性患者可先追蹤觀察,但若積水持續不退或反覆發作,建議評估半劑量光動力等治療,以保護視力並避免組織受損。
2026-10月, 歐洲Euretina視網膜醫學會-黃奕修教授會後新知與心得分享: 認識息肉狀脈絡膜血管病變, 眼底為什麼會漏水、出血? (民眾閱讀版)
息肉狀脈絡膜血管病變(PCV)是亞洲人常見的黃斑部異常新生血管疾病,因血管末端膨大而易反覆造成積水與出血。透過眼底斷層掃描與血管攝影能精準診斷,定期追蹤才能及早穩定病情、守護視力。
2026-10月, 歐洲Euretina視網膜醫學會-黃奕修教授會後新知與心得分享: PCV 治療後,如何長期保護視力? 認識息肉狀脈絡膜血管病變的追蹤、復發與治療安排 (民眾易懂版)
息肉狀脈絡膜血管病變(PCV)在治療積水消退後仍可能反覆發作。透過了解新一代藥物、個人化調整注射間隔與定期追蹤,能及早發現復發警訊,長期穩定守護黃斑部視力。
2026-10月, 歐洲Euretina視網膜醫學會-黃奕修教授會後新知與心得分享: 乾性年齡相關性黃斑部退化(AMD),尤其是地圖狀萎縮(GA)的治療進展與尚待克服的挑戰 (一般民眾版)
乾性黃斑部退化與地圖狀萎縮是導致年長者視力流失的重要原因。目前醫學界正透過補體抑制劑延緩萎縮、提早保護感光細胞,以及發展人工視網膜以重建視覺,為患者帶來多元的治療曙光。
美國歐洲已上市, 可再填充的眼球植入長效藥物傳遞系統, Roche Susvimo PDS 羅氏藥廠舒適眸的適應症有那些呢?
羅氏長效可再填充眼球植入系統 Susvimo(舒適眸)在美歐已獲核准,主要適應症涵蓋濕性黃斑部病變,在美國亦擴及糖尿病黃斑部水腫與糖尿病視網膜病變。
「Roche Susvimo PDS 羅氏藥廠舒適眸, 可再填充的眼球植入長效藥物傳遞系統, 植入後真的半年不用打針?也不用回診嗎?」(問題核心: 減少治療負擔)
介紹長效型眼球植入藥物傳遞系統 Susvimo,雖然能讓多數患者半年僅需補充一次藥物、大幅減輕頻繁打針負擔,但仍須定期回診檢查傷口與視網膜結構,切勿自行中斷追蹤。
「Roche Susvimo PDS 羅氏藥廠舒適眸, 可再填充的眼球植入長效藥物傳遞系統, 會比現在的數月打針方式更好,還是只是比較方便?」(問題核心: 視力效果)
可再填充的眼球植入系統能持續穩定釋放藥物,療效與每月打針相當。它能大幅減少老年性黃斑部病變患者頻繁回診挨針的負擔,避免因治療中斷而導致長期視力下滑。
「Roche Susvimo PDS 羅氏藥廠舒適眸, 可再填充的眼球植入長效藥物傳遞系統, 怎麼放進眼球?會痛嗎?多久能看清楚、恢復生活?」(問題核心: 手術與恢復)
深入解析眼球植入長效裝置 Susvimo 的顯微手術流程、麻醉方式與術後疼痛程度,並詳細說明術後視力恢復歷程,以及各階段傷口照護與避免碰撞的生活活動限制。